Highlighter is on. Drag to highlight text. Click a highlight to remove it.
ALL / Cardiology
Patent ductus arteriosus
Patent ductus arteriosus
Overview- a form of congenital heart defect
- generally classed as 'acyanotic'. However, uncorrected can eventually result in late cyanosis in the lower extremities, termed differential cyanosis
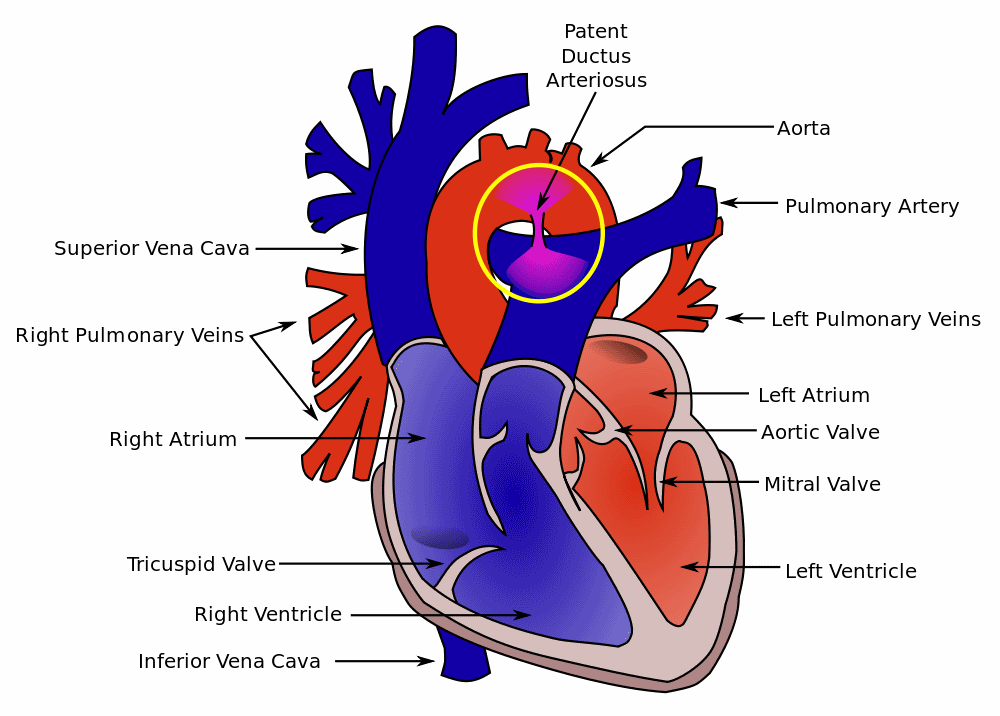
- connection between the pulmonary trunk and descending aorta
- usually, the ductus arteriosus closes with the first breaths due to increased pulmonary flow which enhances prostaglandins clearance
- more common in premature babies, born at high altitude or maternal rubella infection in the first trimester
Features
- left subclavicular thrill
- continuous 'machinery' murmur
- large volume, bounding, collapsing pulse
- wide pulse pressure
- heaving apex beat
Management
Preterm infants
- most centres now recommend initial expectant supportive care rather than early pharmacologic therapy as spontaneous closure often occurs
- if hemodynamically significant ΡDA remains or the infant remains ventilator dependent after one week of age then pharmacological closure is generally recommended:
- ibuprofen, indomethacin or paracetamol
- inhibits prostaglandin synthesis
- given to the infant, not to the mother in the antenatal period
- closes the connection in the majority of cases
- indomethacin use is declining due to increased side-effect profile compared to other drugs
Term infants and children
- indications for closure
- moderate or large ΡDA
- prior episode of endocarditis
- small audible PDΑ
- technique: transcatheter ΡDA closure rather than pharmacological therapy (ibuprofen/indomethacin) which is not effective in term infants
If the PDA is associated with another congenital heart defect amenable to surgery
- prostaglandin E1 is useful to keep the duct open until after surgical repair
+PassMedicine Notes
Overview
- a form of congenital heart defect
- generally classed as 'acyanotic'. However, uncorrected can eventually result in late cyanosis in the lower extremities, termed differential cyanosis
- connection between the pulmonary trunk and descending aorta
- usually, the ductus arteriosus closes with the first breaths due to increased pulmonary flow which enhances prostaglandins clearance
- more common in premature babies, born at high altitude or maternal rubella infection in the first trimester
pdd012.png#
Features- left subclavicular thrill
- continuous 'machinery' murmur
- large volume, bounding, collapsing pulse
- wide pulse pressure
- heaving apex beat
Management
Preterm infants- most centres now recommend initial expectant supportive care rather than early pharmacologic therapy as spontaneous closure often occurs
- if hemodynamically significant ΡDA remains or the infant remains ventilator dependent after one week of age then pharmacological closure is generally recommended:
- ibuprofen, indomethacin or paracetamol
- inhibits prostaglandin synthesis
- given to the infant, not to the mother in the antenatal period
- closes the connection in the majority of cases
- indomethacin use is declining due to increased side-effect profile compared to other drugs
- indications for closure
- moderate or large ΡDA
- prior episode of endocarditis
- small audible PDΑ
- technique: transcatheter ΡDA closure rather than pharmacological therapy (ibuprofen/indomethacin) which is not effective in term infants
- prostaglandin E1 is useful to keep the duct open until after surgical repair