Highlighter is on. Drag to highlight text. Click a highlight to remove it.
ALL / Nephrology
Membranous glomerulonephritis
Membranous glomerulonephritis
Membranous glomerulonephritis is the commonest type of glomerulonephritis in adults and is the third most common cause of end-stage renal failure (ESRF). It usually presents with nephrotic syndrome or proteinuria.Causes
- idiopathic: due to anti-phospholipase A2 antibodies
- infections: hepatitis B, malaria, syphilis
- malignancy (in 5-20%): prostate, lung, lymphoma, leukaemia
- drugs: gold, penicillamine, NSAIDs
- autoimmune diseases: systemic lupus erythematosus (class V disease), thyroiditis, rheumatoid
Diagnosis
- anti-PLA2R antibodies → positive in ~70–80% of idiopathic membranous nephropathy
- screen for secondary causes:
- hepatitis B, C, HIV
- SLE (ANA, anti-dsDNA)
- malignancy (esp. solid tumours: lung, colon, breast)
- drugs (NSAIDs, gold, penicillamine)
- renal biopsy is needed for a definite diagnosis:
- electron microscopy: the basement membrane is thickened with subepithelial electron dense deposits. This creates a 'spike and dome' appearance
Management
- all patients should receive an ACE inhibitor or an angiotensin II receptor blocker (ARB):
- these have been shown to reduce proteinuria and improve prognosis
- immunosuppression
- as many patients spontaneously improve only patient with severe or progressive disease require immunosuppression
- corticosteroids alone have not been shown to be effective. A combination of corticosteroid + another agent such as cyclophosphamide is often used
- consider anticoagulation for high-risk patients
Prognosis - rule of thirds
- one-third: spontaneous remission
- one-third: remain proteinuric
- one-third: develop ESRF
Good prognostic features include female sex, young age at presentation and asymptomatic proteinuria of a modest degree at the time of presentation.
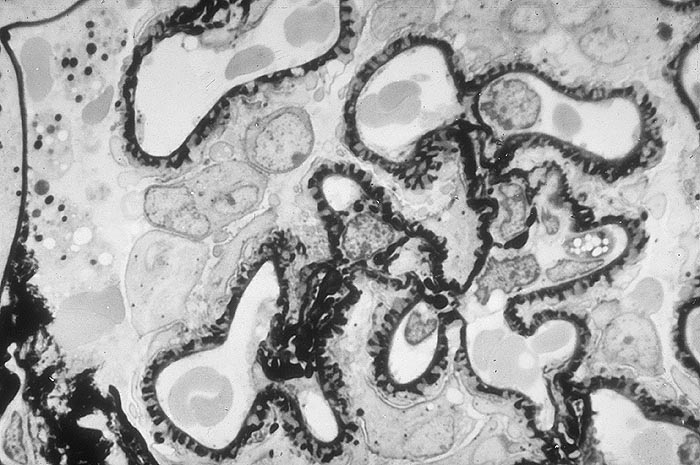
Silver-stained section showing thickened basement membrane, subepithelial spikes
+PassMedicine Notes
Membranous glomerulonephritis is the commonest type of glomerulonephritis in adults and is the third most common cause of end-stage renal failure (ESRF). It usually presents with nephrotic syndrome or proteinuria.
Causes- idiopathic: due to anti-phospholipase A2 antibodies
- infections: hepatitis B, malaria, syphilis
- malignancy (in 5-20%): prostate, lung, lymphoma, leukaemia
- drugs: gold, penicillamine, NSAIDs
- autoimmune diseases: systemic lupus erythematosus (class V disease), thyroiditis, rheumatoid
- anti-PLA2R antibodies → positive in ~70–80% of idiopathic membranous nephropathy
- screen for secondary causes:
- hepatitis B, C, HIV
- SLE (ANA, anti-dsDNA)
- malignancy (esp. solid tumours: lung, colon, breast)
- drugs (NSAIDs, gold, penicillamine)
- renal biopsy is needed for a definite diagnosis:
- electron microscopy: the basement membrane is thickened with subepithelial electron dense deposits. This creates a 'spike and dome' appearance
- all patients should receive an ACE inhibitor or an angiotensin II receptor blocker (ARB):
- these have been shown to reduce proteinuria and improve prognosis
- immunosuppression
- as many patients spontaneously improve only patient with severe or progressive disease require immunosuppression
- corticosteroids alone have not been shown to be effective. A combination of corticosteroid + another agent such as cyclophosphamide is often used
- consider anticoagulation for high-risk patients
- one-third: spontaneous remission
- one-third: remain proteinuric
- one-third: develop ESRF
Good prognostic features include female sex, young age at presentation and asymptomatic proteinuria of a modest degree at the time of presentation.