Atrial fibrillation: cardioversion
Atrial fibrillation: cardioversion
There are two scenarios where cardioversion may be used in atrial fibrillation:- electrical cardioversion as an emergency if the patient is haemodynamically unstable
- electrical or pharmacological cardioversion as an elective procedure where a rhythm control strategy is preferred.
Electrical cardioversion is synchronised to the R wave to prevent delivery of a shock during the vulnerable period of cardiac repolarisation when ventricular fibrillation can be induced.
The notes below refer to cardioversion being used in the elective scenario for rhythm control. The wording of the 2014 NICE guidelines is as follows:
offer rate or rhythm control if the onset of the arrhythmia is less than 48 hours, and start rate control if it is more than 48 hours or is uncertain
Onset < 48 hours
If the atrial fibrillation (AF) is definitely of less than 48 hours onset patients should be heparinised. Patients who have risk factors for ischaemic stroke should be put on lifelong oral anticoagulation. Otherwise, patients may be cardioverted using either:
- electrical - 'DC cardioversion'
- pharmacology - amiodarone if structural heart disease, flecainide or amiodarone in those without structural heart disease
Following electrical cardioversion if AF is confirmed as being less than 48 hours duration then further anticoagulation is unnecessary
Onset > 48 hours
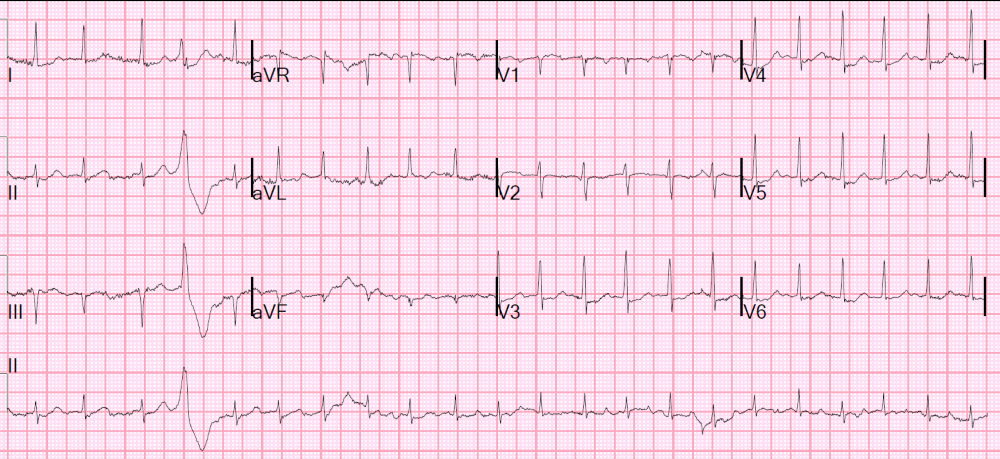
If the patient has been in AF for more than 48 hours then anticoagulation should be given for at least 3 weeks prior to cardioversion. An alternative strategy is to perform a transoesophageal echo (TOE) to exclude a left atrial appendage (LAA) thrombus. If excluded patients may be heparinised and cardioverted immediately.
NICE recommend electrical cardioversion in this scenario, rather than pharmacological.
If there is a high risk of cardioversion failure (e.g. Previous failure or AF recurrence) then it is recommend to have at least 4 weeks amiodarone or sotalol prior to electrical cardioversion
Following electrical cardioversion patients should be anticoagulated for at least 4 weeks. After this time decisions about anticoagulation should be taken on an individual basis depending on the risk of recurrence
+PassMedicine Notes
- electrical cardioversion as an emergency if the patient is haemodynamically unstable
- electrical or pharmacological cardioversion as an elective procedure where a rhythm control strategy is preferred.
Electrical cardioversion is synchronised to the R wave to prevent delivery of a shock during the vulnerable period of cardiac repolarisation when ventricular fibrillation can be induced.
The notes below refer to cardioversion being used in the elective scenario for rhythm control. The wording of the 2014 NICE guidelines is as follows:
offer rate or rhythm control if the onset of the arrhythmia is less than 48 hours, and start rate control if it is more than 48 hours or is uncertain
Onset < 48 hours
If the atrial fibrillation (AF) is definitely of less than 48 hours onset patients should be heparinised. Patients who have risk factors for ischaemic stroke should be put on lifelong oral anticoagulation. Otherwise, patients may be cardioverted using either:- electrical - 'DC cardioversion'
- pharmacology - amiodarone if structural heart disease, flecainide or amiodarone in those without structural heart disease
Following electrical cardioversion if AF is confirmed as being less than 48 hours duration then further anticoagulation is unnecessary
Onset > 48 hours
If the patient has been in AF for more than 48 hours then anticoagulation should be given for at least 3 weeks prior to cardioversion. An alternative strategy is to perform a transoesophageal echo (TOE) to exclude a left atrial appendage (LAA) thrombus. If excluded patients may be heparinised and cardioverted immediately.
NICE recommend electrical cardioversion in this scenario, rather than pharmacological.
If there is a high risk of cardioversion failure (e.g. Previous failure or AF recurrence) then it is recommend to have at least 4 weeks amiodarone or sotalol prior to electrical cardioversion
Following electrical cardioversion patients should be anticoagulated for at least 4 weeks. After this time decisions about anticoagulation should be taken on an individual basis depending on the risk of recurrence