Highlighter is on. Drag to highlight text. Click a highlight to remove it.
ALL / Gastroenterology
Achalasia
Achalasia
Failure of oesophageal peristalsis and of relaxation of the lower oesophageal sphincter (LOS) due to degenerative loss of ganglia from the myenteric (Auerbach's) plexus i.e. LOS contracted, oesophagus above dilated. Achalasia typically presents in middle-age and is equally common in men and women.Clinical features
- dysphagia of BOTH liquids and solids
- typically variation in severity of symptoms
- heartburn
- regurgitation of food
- may lead to cough, aspiration pneumonia etc
- malignant change in small number of patients
Investigations
- oesophageal manometry
- excessive LOS tone which doesn't relax on swallowing
- considered the most important diagnostic test
- barium swallow
- shows grossly expanded oesophagus, fluid level
- 'bird's beak' appearance
- chest x-ray
- wide mediastinum
- fluid level
Treatment
- pneumatic (balloon) dilation is increasingly the preferred first-line option
- less invasive and quicker recovery time than surgery
- patients should be a low surgical risk as surgery may be required if complications occur
- surgical intervention with a Heller cardiomyotomy should be considered if recurrent or persistent symptoms
- intra-sphincteric injection of botulinum toxin is sometimes used in patients who are a high surgical risk
- drug therapy (e.g. nitrates, calcium channel blockers) has a role but is limited by side-effects
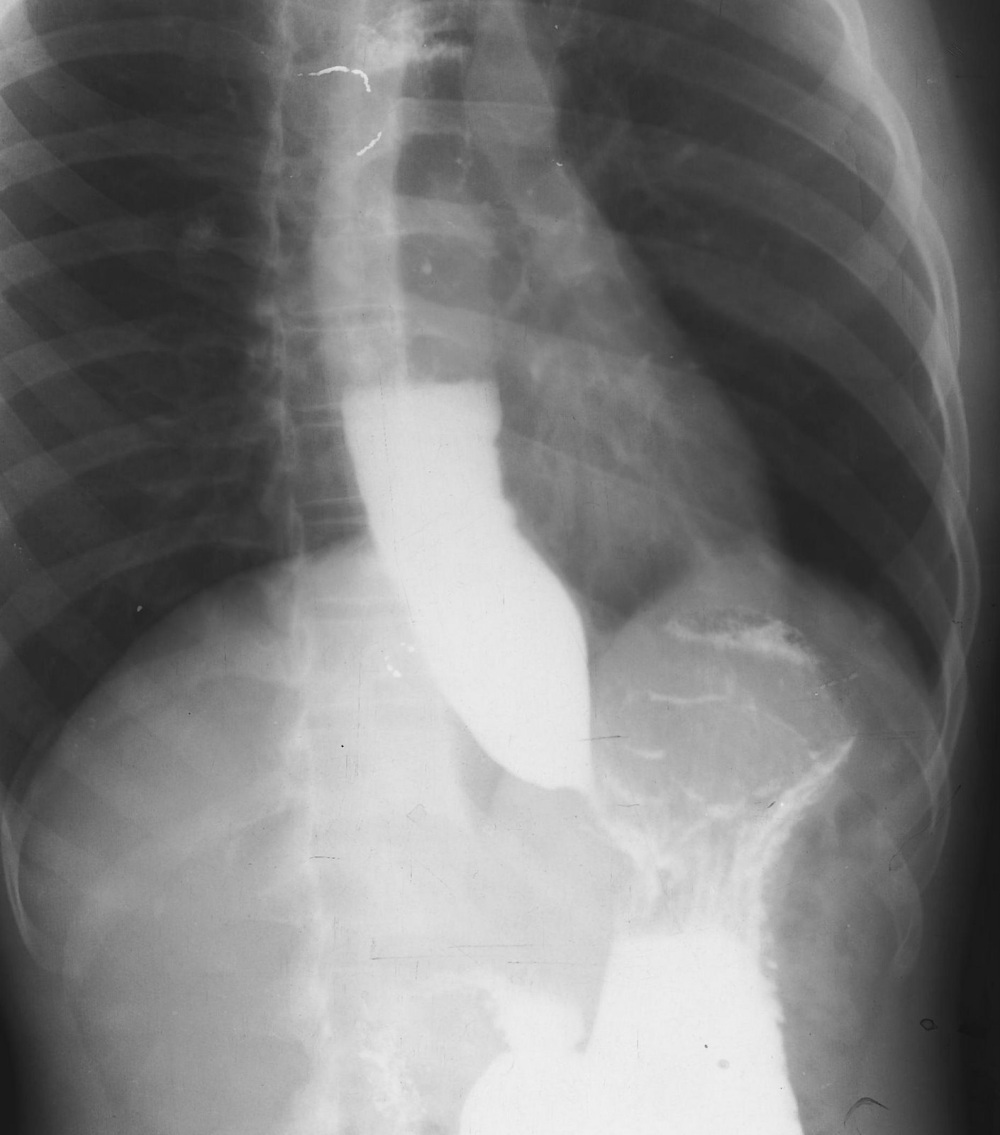
This film demonstrates the classical
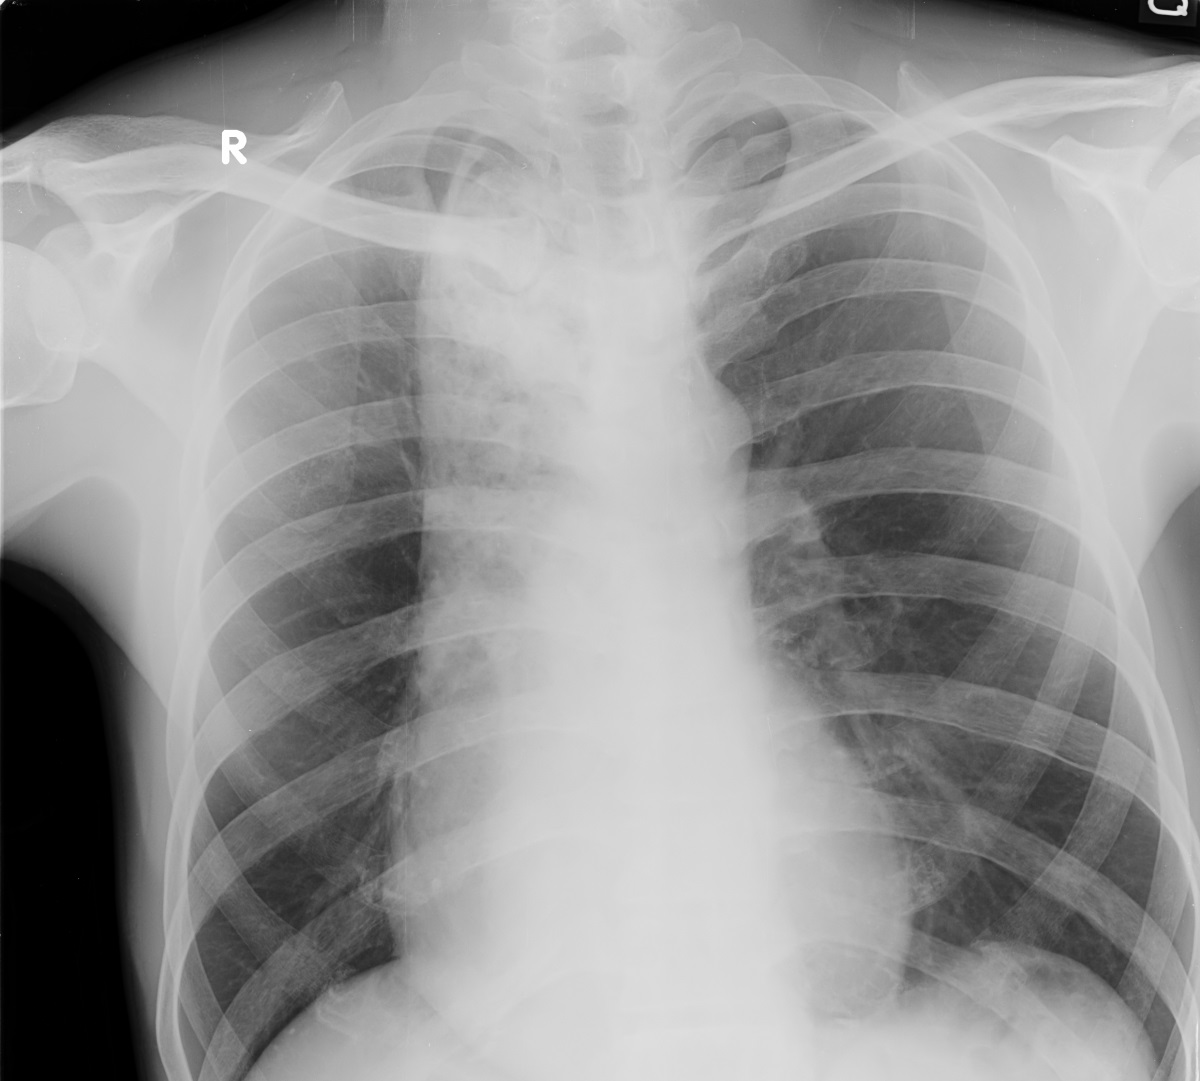
Mediastinal widening secondary to achalasia. An air-fluid level can sometimes be seen on CXR but it is not visible on this film
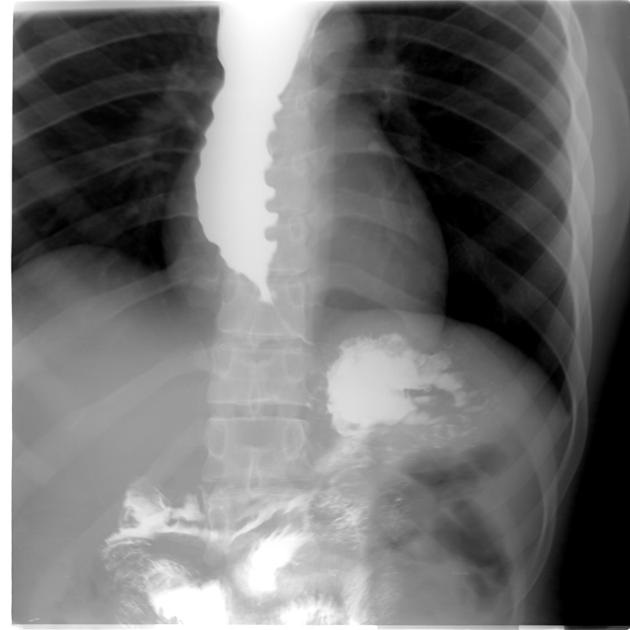
>Barium swallow - grossly dilated filled oesophagus with a tight stricture at the gastroesophageal junction resulting in a
+PassMedicine Notes
Failure of oesophageal peristalsis and of relaxation of the lower oesophageal sphincter (LOS) due to degenerative loss of ganglia from the myenteric (Auerbach's) plexus i.e. LOS contracted, oesophagus above dilated. Achalasia typically presents in middle-age and is equally common in men and women.
Clinical features- dysphagia of BOTH liquids and solids
- typically variation in severity of symptoms
- heartburn
- regurgitation of food
- may lead to cough, aspiration pneumonia etc
- malignant change in small number of patients
- oesophageal manometry
- excessive LOS tone which doesn't relax on swallowing
- considered the most important diagnostic test
- barium swallow
- shows grossly expanded oesophagus, fluid level
- 'bird's beak' appearance
- chest x-ray
- wide mediastinum
- fluid level
- pneumatic (balloon) dilation is increasingly the preferred first-line option
- less invasive and quicker recovery time than surgery
- patients should be a low surgical risk as surgery may be required if complications occur
- surgical intervention with a Heller cardiomyotomy should be considered if recurrent or persistent symptoms
- intra-sphincteric injection of botulinum toxin is sometimes used in patients who are a high surgical risk
- drug therapy (e.g. nitrates, calcium channel blockers) has a role but is limited by side-effects
