Highlighter is on. Drag to highlight text. Click a highlight to remove it.
ALL / Cardiology
Ventricular tachycardia
Ventricular tachycardia
Ventricular tachycardia (VT) is broad-complex tachycardia originating from a ventricular ectopic focus. It has the potential to precipitate ventricular fibrillation and hence requires urgent treatment.There are two main types of VT:
- monomorphic VT: most commonly caused by myocardial infarction
- polymorphic VT: A subtype of polymorphic VT is torsades de pointes which is precipitated by prolongation of the QT interval. The causes of a long QT interval are listed below
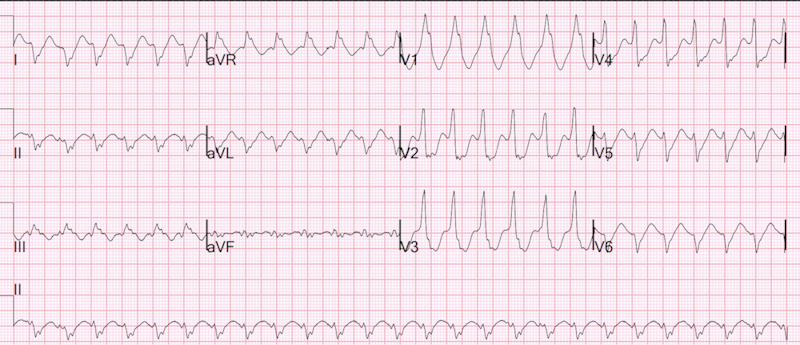
This ECG shows a broad-complex tachycardia at ~180 bpm with no visible P waves, regular rhythm, and QRS morphology not consistent with typical bundle branch block. This is ventricular tachycardia (VT) until proven otherwise. © Image used on license from Dr Smith, University of Minnesota
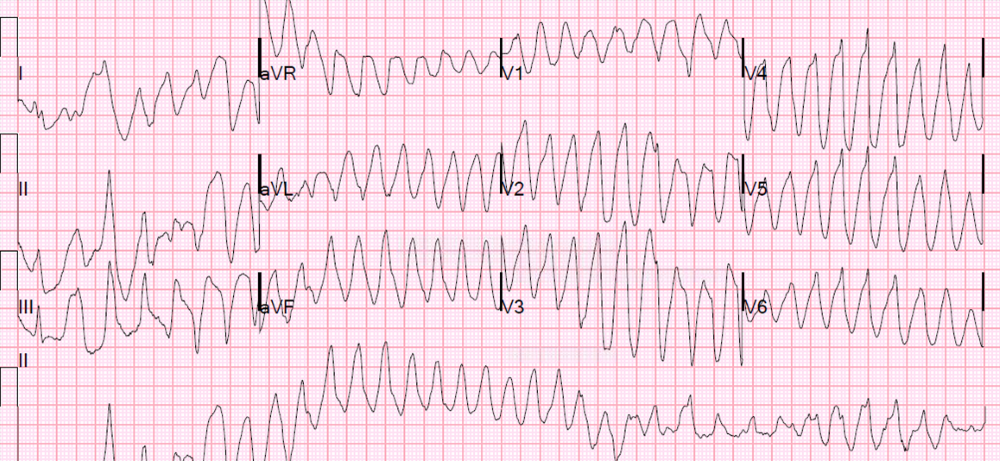
Polymorphic VT - © Image used on license from Dr Smith, University of Minnesota
Causes of a prolonged QT interval
| Congenital | Drugs | Other |
|---|---|---|
|
Management
If the patient has adverse signs (systolic BP < 90 mmHg, chest pain, heart failure) then immediate cardioversion is indicated. In the absence of such signs antiarrhythmics may be used. If these fail, then electrical cardioversion may be needed with synchronised DC shocks
Drug therapy
- amiodarone: ideally administered through a central line
- lidocaine: use with caution in severe left ventricular impairment
- procainamide
Verapamil should NOT be used in VT
If drug therapy fails
- electrophysiological study (EPS)
- implant able cardioverter-defibrillator (ICD) - this is particularly indicated in patients with significantly impaired LV function
+PassMedicine Notes
Ventricular tachycardia (VT) is broad-complex tachycardia originating from a ventricular ectopic focus. It has the potential to precipitate ventricular fibrillation and hence requires urgent treatment.
There are two main types of VT:- monomorphic VT: most commonly caused by myocardial infarction
- polymorphic VT: A subtype of polymorphic VT is torsades de pointes which is precipitated by prolongation of the QT interval. The causes of a long QT interval are listed below
Causes of a prolonged QT interval
Congenital _ Drugs _ Other|- Jervell-Lange-Nielsen syndrome (includes deafness and is due to an abnormal potassium channel)
- Romano-Ward syndrome (no deafness) _
- amiodarone, sotalol, class 1a antiarrhythmic drugs
- tricyclic antidepressants, fluoxetine
- chloroquine
- terfenadine
- erythromycin _
- electrolyte: hypocalcaemia, hypokalaemia, hypomagnesaemia
- acute myocardial infarction
- myocarditis
- hypothermia
- subarachnoid haemorrhage|
Management
If the patient has adverse signs (systolic BP < 90 mmHg, chest pain, heart failure) then immediate cardioversion is indicated. In the absence of such signs antiarrhythmics may be used. If these fail, then electrical cardioversion may be needed with synchronised DC shocks
Drug therapy- amiodarone: ideally administered through a central line
- lidocaine: use with caution in severe left ventricular impairment
- procainamide
Verapamil should NOT be used in VT
If drug therapy fails- electrophysiological study (EPS)
- implant able cardioverter-defibrillator (ICD) - this is particularly indicated in patients with significantly impaired LV function